A discolored toenail can trigger two very different reactih conditions can change a nail’s color, shape, or texture, but they require dramatically different treatment. Toenail fungus is common, persistent, and usually manageable. Nail melanoma is rare, potentially life-threatening, and best treated as early as possible.
The difficult part is that toenails are not great communicators. They tend to express everythingfrom tight shoes to infection to cancerwith the same limited vocabulary of streaks, spots, thickening, and cracking. You cannot reliably diagnose either condition from a photograph or bathroom inspection alone. However, understanding their typical patterns can help you recognize when routine care is reasonable and when a dermatologist should examine the nail promptly.
Toenail Melanoma vs. Fungus at a Glance
| Feature | Toenail Melanoma | Toenail Fungus |
|---|---|---|
| Typical color | Brown, black, or occasionally reddish pigment, often forming a vertical band | Yellow, white, tan, brown, or occasionally darker discoloration |
| Number of nails | Often affects one nail | May begin in one nail but commonly spreads to several |
| Nail texture | May initially remain smooth; later may split, lift, crack, bleed, or develop a growth | Frequently becomes thick, brittle, crumbly, distorted, or separated from the nail bed |
| Location of change | Often begins near the nail matrix and runs from the base toward the tip | Often begins near the outer edge or tip and gradually moves inward |
| Surrounding skin | Dark pigment may extend onto the cuticle or nearby skin | Skin may be scaly, itchy, or irritated, especially when athlete’s foot is present |
| Diagnosis | Nail examination, dermoscopy, and sometimes a nail matrix or nail-bed biopsy | Nail clipping or scraping examined by microscopy, staining, culture, or molecular testing |
| Main treatment | Surgical removal of the cancer, with additional treatment based on its stage | Topical or oral antifungal medication, often combined with nail trimming or debridement |
These are tendencies, not diagnostic rules. Fungus can darken a nail, melanoma can appear without obvious pigment, and both conditions can affect the nail’s structure. Consider the table a useful mapnot a medical verdict delivered by your big toe.
What Is Toenail Fungus?
Toenail fungus, medically known as onychomycosis, is an infection of the nail plate, nail bed, or surrounding nail structures. Dermatophytesthe same general group of fungi responsible for athlete’s footcause many cases. Yeasts and other molds can also infect nails.
The organisms thrive in warm, damp environments. Sweaty shoes, locker-room floors, public showers, shared nail tools, and untreated athlete’s foot can all help fungus reach a nail. Small cracks caused by tight footwear, sports, aging, or repeated trauma provide convenient entry points.
Common signs of fungal toenails
- Yellow, white, tan, or brown discoloration
- A nail that becomes thicker than the others
- Crumbly, ragged, or brittle edges
- Chalky white areas on the nail surface
- Debris building up beneath the nail
- Separation of the nail from the nail bed
- An unpleasant odor
- Pressure, tenderness, or discomfort inside shoes
Fungus frequently starts near the tip or side of a toenail and progresses toward the base. The big toe and second toe are common targets. Several nails may eventually become involved, although an early infection can certainly affect only one.
What Is Toenail Melanoma?
Toenail melanoma is a melanoma arising within the nail unit, often in the nail matrix where new nail cells are produced. It is commonly described as subungual melanoma or nail apparatus melanoma and is usually associated with the acral lentiginous melanoma subtype.
Unlike many melanomas that develop on sun-exposed skin, nail melanoma is not strongly associated with ultraviolet exposure. It can occur in people of any skin tone. Awareness is particularly important among people with darker skin because acral and nail melanomas make up a larger proportion of melanomas diagnosed in these populations.
Possible warning signs of nail melanoma
- A new brown or black vertical band running from the base toward the tip
- A band that gradually becomes wider, especially near the cuticle
- Uneven pigment with multiple shades of brown or black
- Blurred, irregular, or poorly defined borders
- Pigment spreading onto the cuticle or skin beside the nail
- Splitting, cracking, lifting, or distortion without a clear explanation
- A bump, ulcer, or mass beneath the nail
- Bleeding that is not explained by a recent injury
- A persistent nail abnormality that does not grow out
The extension of pigment from the nail onto nearby skin is often called the Hutchinson sign. It deserves prompt medical assessment, although benign conditions can sometimes create a similar appearance. Some nail melanomas are amelanotic, meaning they contain little visible dark pigment. These may look pink, red, swollen, damaged, or wart-like instead of forming the familiar dark line.
How to Tell Melanoma From Fungus
Look at the pattern, not merely the color
Fungal discoloration is often diffuse, cloudy, yellowish, or concentrated beneath the outer portion of the nail. Melanoma more commonly creates a lengthwise band that begins near the nail’s growth center. A band that changes, becomes irregular, or widens near the base is more concerning than a stable, narrow line that has remained identical for years.
Count the affected nails
Fungus often spreads among toes, particularly when athlete’s foot is also present. Melanoma generally develops in a single nail. One abnormal nail is not automatically cancer, but a solitary and steadily changing pigmented nail deserves more attention than several similarly thick, yellow nails.
Notice what happens to the nail surface
Fungus commonly produces obvious thickening, crumbling, scaling, and debris. Early nail melanoma may alter pigment before significantly changing texture. As melanoma progresses, however, the nail can crack, split, lift, bleed, or become deformed. Texture alone cannot settle the question.
Watch whether a mark grows out
A bruise under the toenail usually follows an injury, running, hiking, or pressure from tight shoes. As the nail grows, the discolored area should gradually move toward the tip. Melanoma pigment generally remains connected to the nail’s base because the abnormality originates in tissue that continues producing the nail.
Toenails grow slowly, so a bruise may take many months to disappear. Photographing the nail in consistent lighting every four weeks can help document movement or change. A mark that stays anchored near the cuticle, widens, or develops irregular borders should be examined rather than endlessly photographed like a very uncooperative houseplant.
How Doctors Diagnose an Abnormal Toenail
A clinician begins by asking when the change appeared, whether it has evolved, whether the toe was injured, and whether other nails or areas of skin are affected. Medical conditions, medications, occupation, sports, family history, and previous antifungal treatment may also provide clues.
Testing for toenail fungus
Many nail disorders resemble onychomycosis, including psoriasis, eczema, bacterial infections, repeated shoe trauma, and benign age-related changes. For that reason, visual inspection alone can lead to unnecessary treatment.
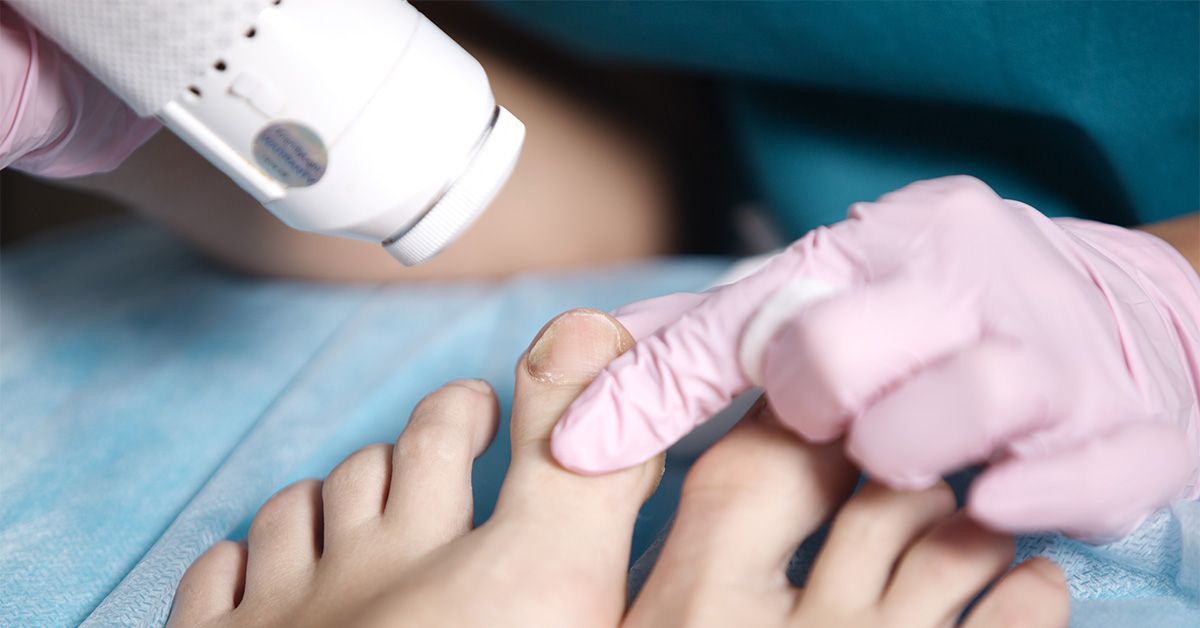
A dermatologist, podiatrist, or other qualified clinician may clip part of the nail, scrape material from beneath it, or collect surface debris. Testing may include:
- Potassium hydroxide microscopy: A rapid method used to look for fungal structures.
- Fungal culture: Helps identify the organism but may take several weeks and can occasionally be falsely negative.
- Periodic acid-Schiff staining: Allows a laboratory specialist to identify fungal material in nail clippings.
- Polymerase chain reaction testing: Detects fungal genetic material and may provide faster organism identification when available.
Confirming fungus is especially valuable before starting oral medication, because treatment lasts for weeks, can interact with other drugs, and is not appropriate for every patient.
Testing for nail melanoma
A dermatologist may examine the nail with a dermatoscope, a magnifying device that reveals pigment patterns not easily seen with the naked eye. Clinical examination and dermoscopy can determine how suspicious a lesion appears, but they cannot always provide a final answer.
A biopsy is the definitive diagnostic test. Depending on the location of the abnormality, the dermatologist or nail surgeon may sample the nail matrix, nail bed, or another portion of the nail unit. The tissue is then examined by a pathologist. Nail biopsies require careful planning because the matrix creates the nail plate, and unnecessary damage may cause permanent nail deformity. Nevertheless, avoiding a needed biopsy simply to protect the appearance of the nail is not a sensible trade when melanoma is a realistic possibility.
Causes and Risk Factors
Why toenail fungus develops
Fungal organisms reach the nail through small openings in the skin or nail structure. Risk increases with age because toenails grow more slowly and circulation may decline. Additional risk factors include:
- Current or recurring athlete’s foot
- Excessive sweating
- Tight, enclosed, or poorly ventilated footwear
- Repeated nail trauma from work, sports, or shoes
- Walking barefoot in communal wet areas
- Sharing towels, socks, shoes, or nail tools
- Diabetes or reduced blood flow to the feet
- Psoriasis or other chronic nail disorders
- A weakened immune system
- Living with someone who has a fungal nail infection
Why nail melanoma develops
The exact cause of nail melanoma remains uncertain. It begins when pigment-producing melanocytes in the nail unit grow abnormally and form a malignant tumor. Unlike conventional sun-related melanoma, nail melanoma is not considered primarily caused by tanning or routine sunlight exposure.
Older age, a personal or family history of melanoma, and darker skin pigmentation are associated with increased clinical concern. Previous trauma is sometimes reported, but researchers have not established that an ordinary stubbed toe directly causes melanoma. An injury may simply draw attention to a lesion that was already present.
Treatment for Toenail Fungus
Treatment depends on the organism, the number of affected nails, the percentage of nail involved, whether the nail matrix is affected, and the patient’s overall health. Mild cases may be treated topically, while extensive disease often responds better to oral therapy.
Topical antifungal medicines
Prescription options include ciclopirox lacquer, efinaconazole solution, and tavaborole solution. These products are applied regularlyoften dailyand treatment of a toenail may continue for approximately 48 weeks. Topical therapy generally causes fewer whole-body side effects but is less effective when the nail is very thick, several nails are infected, or fungus has reached the matrix.
Trimming, thinning, or professionally debriding the nail can help medication penetrate. Regular drugstore creams may treat fungal skin around the toe but often cannot reach organisms living deep inside a thick nail plate.
Oral antifungal medicines
Oral terbinafine is commonly used as first-line treatment for confirmed toenail onychomycosis when no contraindication exists. A typical prescribed course for toenails lasts about 12 weeks. Itraconazole and, in selected situations, other antifungal medicines may be considered.
Oral antifungals can interact with other medications and may cause side effects. Terbinafine is not suitable for people with active or chronic liver disease, and clinicians generally review liver history and obtain baseline liver-function tests before treatment. Patients should report symptoms such as persistent nausea, unusual fatigue, dark urine, pale stools, severe rash, or yellowing of the skin or eyes.
Why improvement takes so long
Antifungal medication may eliminate the infection before the toenail looks normal. The damaged section must physically grow out, which can take a year or longer for a big toenail. A clear strip appearing near the base is often a better early sign of progress than the stubborn discoloration at the tip.
Recurrence is common. Treating athlete’s foot, keeping feet dry, rotating shoes, changing socks, disinfecting nail tools, and avoiding barefoot trips through public showers can reduce reinfection.
Treatment for Toenail Melanoma
Surgery is the primary treatment for localized nail melanoma. The surgeon removes the melanoma along with an appropriate margin of surrounding tissue. This may require removal of the nail plate and affected portions of the nail matrix or nail bed.
Amputation was historically used more often, but it is not automatically necessary for every nail melanoma. The operation depends on the tumor’s thickness, depth, position, and involvement of nearby bone or tissue. Specialized teams may use tissue-preserving procedures when medically appropriate.
For invasive melanoma, the care team may discuss sentinel lymph node biopsy to check whether cancer has reached nearby lymph nodes. Melanoma that has spread or carries a significant risk of recurrence may require immunotherapy, targeted therapy when relevant mutations are present, radiation, or other oncology treatments. Treatment should be individualized by dermatologic surgeons, surgical oncologists, medical oncologists, and other melanoma specialists.
When to See a Doctor
Arrange a prompt dermatology evaluation when you notice:
- A new brown or black stripe in one nail
- A stripe that is widening, darkening, or becoming irregular
- Pigment extending onto the cuticle or nearby skin
- Bleeding, ulceration, or a growth beneath the nail
- Nail destruction without a convincing history of trauma
- A dark mark that does not move toward the tip as the nail grows
- A presumed fungal infection that continues changing despite appropriate treatment
People with diabetes, poor circulation, neuropathy, immune suppression, or significant foot pain should also seek professional care rather than aggressively trimming or filing the nail at home.
Experience-Based Lessons: What These Nail Changes Can Feel Like in Real Life
The following scenarios are educational composites based on common patient experiences. They are not accounts of specific individuals and should not be used for self-diagnosis.
Experience 1: The runner with a black toenail
After training for a half-marathon, a runner notices a dark patch beneath the second toenail. The toe was sore after a downhill workout, and the shoes felt unusually tight. Over the next two months, the patch slowly travels toward the nail’s outer edge while a clear nail grows behind it.
This pattern is more consistent with a subungual hematomaa collection of blood caused by repeated impactthan with melanoma. The useful clues are the clear triggering event and the fact that the discoloration moves with nail growth. Even so, the runner photographs the toe monthly. Had the pigment stayed attached to the base, widened, or spread onto the cuticle, a dermatology appointment would have been the wiser finish line.
Experience 2: The “fungus” treatment that required patience
Another person develops two thick, yellow toenails after months of wearing heavy work boots. The skin between the toes is flaky and itchy. A clinician collects nail material, confirms a fungal infection, and prescribes treatment. The itching improves quickly, but the nails still look awful after three months.
This is where frustration often defeats treatment. Killing fungus does not instantly replace damaged keratin. Toenails are slow historians; they preserve months of previous damage until that section grows out. A narrow band of healthier nail near the cuticle shows that the plan may be working. Continued foot care, medication adherence, and treatment of athlete’s foot are more useful than switching remedies every two weeks because an online advertisement promised “crystal-clear nails by Friday.”
Experience 3: The single vertical band that kept changing
A person notices a thin brown stripe on one big toenail. There is no known injury, and the other nails look normal. Six months later, the stripe is wider near the cuticle and contains several shades of brown. A tiny amount of pigment appears on the nearby skin.
Because the nail is neither thick nor crumbly, the person questions whether fungus makes sense. Rather than beginning another over-the-counter treatment, they see a dermatologist. Dermoscopy shows an irregular pigment pattern, and a carefully planned biopsy is recommended.
The lesson is not that every nail stripe is melanoma. Many vertical bands are benign, especially when they are stable or appear in several nails. The lesson is that evolution matters. A changing band affecting one nail, particularly when it widens at the base or extends onto surrounding skin, should not be managed through guesswork.
Experience 4: The importance of asking for a second look
Some people spend months assuming a nail problem is cosmetic because it does not hurt. Others feel embarrassed about showing their feet or worry that requesting a specialist will sound dramatic. Yet neither fungus nor melanoma must be painful in its early stages.
When a nail continues to change, it is reasonable to ask what diagnosis is being considered and whether testing is needed. Useful questions include: “Should this be tested for fungus?” “Does the pigment pattern require dermoscopy?” and “At what point would you recommend a biopsy?” A thoughtful clinician will not be offended by clear questions. Good medical care is a conversation, not a talent show in which the patient wins points for staying quiet.
Together, these experiences highlight three practical habits: document unexplained nail changes, avoid assuming that every abnormal nail is fungal, and seek timely evaluation when a single nail develops progressive pigment or structural damage. Most abnormal toenails are not melanoma, but the cost of checking a suspicious change is far lower than the cost of overlooking one.
Conclusion
Toenail fungus and nail melanoma can overlap in appearance, but their usual patterns offer valuable clues. Fungus commonly creates thick, yellow, brittle nails with debris and may spread across several toes. Nail melanoma more often affects one nail and may appear as a changing vertical band, irregular pigment, surrounding skin discoloration, bleeding, or unexplained nail destruction.
No visual checklist can replace proper testing. Nail scrapings or clippings can confirm onychomycosis, while a suspicious pigmented lesion may require dermoscopy and biopsy. When uncertainty existsespecially with a new or evolving dark stripechoose an examination over a prolonged experiment with home remedies.